

The two main foot pulses names are dorsalis pedis and posterior tibial. The dorsalis pedis pulse is found on the top of the foot, while the posterior tibial pulse is located behind the inner ankle bone. Healthcare professionals check these pulse points to assess blood flow to the lower extremities.
If you are studying anatomy, learning nursing skills, or trying to understand a circulation examination, knowing these locations can make the subject easier. This guide explains the names of foot pulses, their anatomical landmarks, how clinicians assess them, and what weak or difficult-to-find pulses may mean. It is educational information, not a substitute for a medical examination.
How to find and assess a pedal pulse
A pedal pulse is the pulse felt in the foot. It reflects the pressure wave produced when the heart pumps blood through the arteries. During a vascular examination, healthcare professionals commonly check the dorsalis pedis and posterior tibial pulses on both feet to assess peripheral circulation.
The examination involves more than finding a heartbeat beneath the skin. Clinicians also compare pulse strength between the left and right feet and consider symptoms, skin temperature, color, sensation, swelling, and other examination findings. A single pulse finding cannot establish whether a person has a vascular disease.
Two possible pedal pulse positions to check
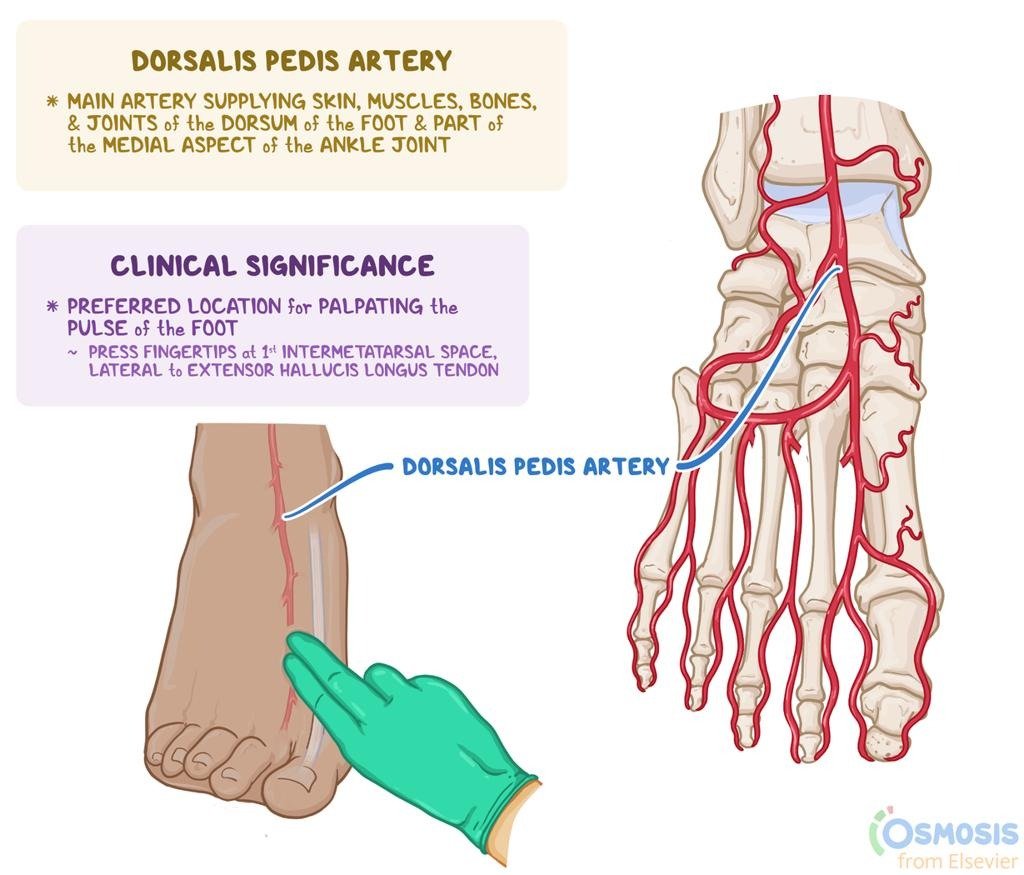
1. Dorsalis pedis pulse
Location: Top of the foot
This pulse is usually felt on the dorsal surface, near the center of the foot and slightly to the outer side of the tendon that extends the big toe. Its exact position can vary between individuals.
2. Posterior tibial pulse
Location: Behind the inner ankle bone
This pulse is palpated in the soft groove between the medial malleolus and the Achilles tendon. It provides another important site for assessing arterial blood flow to the foot.
These are the two standard pedal pulse locations most relevant to someone searching for foot pulse names. Although both are used to assess circulation, they follow different arteries and are felt at different anatomical landmarks.
Posterior tibial
The posterior tibial artery travels down the back of the lower leg and passes behind the medial malleolus, the prominent bone on the inner ankle. Its pulse can be felt just behind and slightly below this bone, toward the Achilles tendon. Swelling and anatomical differences can make palpation more difficult.
During a clinical examination, the healthcare professional uses the fingertips to assess the pulse and compares the result with the opposite foot. A pulse that is absent or weaker than expected may warrant further evaluation, particularly when accompanied by pain, cool skin, discoloration, or a wound that is not healing.
Dorsalis pedis
The dorsalis pedis artery supplies the dorsal, or upper, surface of the foot. It is generally examined near the middle of the foot, alongside the tendon that extends the big toe. Because the artery’s position varies, the pulse may not be found at precisely the same point in every person.
A clinician usually applies gentle fingertip pressure and adjusts the position slightly if the pulse is difficult to detect. The artery can be absent or unusually positioned because of natural anatomical variation. Therefore, an undetectable dorsalis pedis pulse alone does not automatically establish peripheral artery disease.
Physical Exam: Pedal Pulse Assessment
A pedal pulse assessment is part of a broader examination of circulation in the feet and lower legs. It can be important when evaluating people with diabetes, suspected peripheral artery disease, lower-limb injuries, or foot wounds. Healthcare professionals document the pulse site, strength, and symmetry alongside other relevant clinical findings.
The examination is not simply a matter of deciding whether a pulse is present or absent. The patient’s symptoms, medical history, temperature and color of the skin, and findings from additional tests all contribute to the clinical interpretation. When manual palpation is inconclusive, a Doppler device may help detect arterial blood flow.
Understanding the foot pulse names
The term pedal pulse is a general name for a pulse detected in the foot. The terms dorsalis pedis and posterior tibial identify the two principal pulse sites routinely assessed during a foot circulation examination.
| Foot pulse name | Artery | Where it is checked |
| Dorsalis pedis | Dorsalis pedis artery | Top of the foot |
| Posterior tibial | Posterior tibial artery | Behind the inner ankle bone |
These names refer to specific anatomical structures rather than different heartbeats. Both pulses originate from the arterial circulation supplying the lower extremities, but they can provide information about blood flow through different parts of the foot.
How clinicians assess a pedal pulse
A healthcare professional typically exposes the foot, positions it comfortably, and uses the fingertips to palpate the appropriate site. The examiner may compare the two feet, note differences in pulse strength, and inspect the skin for changes in color or temperature. The assessment is interpreted alongside the patient’s overall clinical condition.
When the pulse cannot be felt, a trained professional may use handheld Doppler ultrasound or arrange additional vascular testing. These tools can help clarify whether blood is flowing through the artery when manual examination is difficult. A person should not rely on self-palpation to rule out a circulation problem.
Other foot arteries and anatomical branches
The anterior tibial artery supplies the front of the lower leg and continues into the foot as the dorsalis pedis artery in typical anatomy. The posterior tibial artery supplies the posterior lower leg and gives rise to the medial and lateral plantar arteries, which contribute to the blood supply of the sole.
Other vessels, including branches of the fibular (peroneal) artery, contribute to the circulation of the ankle and foot. These vessels matter when studying foot anatomy, but they are not usually presented as the two principal routine pedal pulse points. The names of arteries and the names of palpable pulse sites are related but not interchangeable in every context.
Check foot temperature and color
Pulse findings should be interpreted alongside the appearance and feel of the foot. Normal warmth and color can be reassuring, but neither finding guarantees that circulation is healthy. Likewise, cool skin can result from environmental conditions and does not independently diagnose an arterial blockage.
During an assessment, a clinician may check for pallor, bluish discoloration, unusual coldness, delayed capillary refill, reduced sensation, or wounds that heal slowly. The importance of each sign depends on its severity, duration, and relationship to other symptoms. Comparing both feet can help identify changes that deserve further examination.
What can make a foot pulse difficult to feel?
Several factors can affect the ability to palpate a pedal pulse:
- Anatomical variation: The artery may follow a different course or be difficult to locate at its typical landmark.
- Swelling: Edema around the ankle or foot can make examination more difficult.
- Technique: Incorrect finger placement or excessive pressure may prevent a pulse from being detected.
- Cold conditions: Temperature can affect peripheral blood vessels and the examination.
- Reduced arterial blood flow: Narrowed or blocked arteries can weaken a pulse.
- Body structure: Differences in tissue depth can affect how easily an artery is felt.
A difficult-to-find pulse is not proof of poor circulation. If a pulse seems absent, a trained healthcare professional can repeat the assessment, examine the other foot, and decide whether further testing is appropriate.
What does a weak or absent foot pulse mean?
A weak or absent pedal pulse may be associated with reduced arterial blood flow, including peripheral artery disease. However, anatomical variation and difficulties with manual examination can produce similar findings. A clinician considers the whole examination instead of diagnosing a condition from one pulse alone.
Persistent differences between feet, especially when combined with pain during walking, nonhealing wounds, or skin discoloration, should be evaluated by a healthcare professional. Sudden severe pain with a newly cold, pale, numb, or weak foot can indicate an acute circulation emergency and requires immediate emergency care.
Pedal Pulse
The term pedal pulse is commonly used in nursing, emergency medicine, podiatry, and vascular assessment. It refers to the pulse detected in the foot, most often at the dorsalis pedis or posterior tibial artery. Healthcare professionals use these sites when examining circulation in the lower extremities.
Pedal pulse findings can help guide decisions about additional examinations. Depending on the clinical situation, a healthcare professional may assess blood pressure at the ankle and arm, use Doppler ultrasound, or order further vascular investigations. A normal-feeling pulse is useful information, but it does not rule out every circulation disorder.
How to check a foot pulse safely
For general educational purposes, the main pulse landmarks are straightforward to remember: the dorsalis pedis is on top of the foot, and the posterior tibial is behind the inner ankle bone. In a clinical setting, the examiner uses gentle fingertip pressure and adjusts the position according to the patient’s anatomy.
Do not press forcefully, particularly over a painful or injured area. If you cannot locate a pulse, repeated searching at home is not a reliable way to determine whether blood flow is adequate. A healthcare professional can assess both feet and use appropriate equipment when needed.
Why compare the left and right feet?
Comparing corresponding pulse sites on both feet can help a clinician recognize asymmetry. For example, if one pulse is easily detected and the other is not, the difference may prompt a closer examination of arterial blood flow, particularly when symptoms are also present.
However, pulses do not always feel identical in healthy people, and an anatomical variation can affect one side. The comparison should therefore be interpreted with the patient’s history, examination findings, and any indicated vascular tests rather than used as a stand-alone diagnostic rule.
Tests used when a pulse is difficult to detect
A healthcare professional may use a handheld Doppler ultrasound device to detect blood flow through an artery. This is especially helpful when the pulse cannot be reliably felt by hand. The device provides additional information, but the result must still be interpreted in the context of the examination.
Another test is the ankle-brachial index (ABI), which compares systolic blood pressure at the ankle with systolic blood pressure in the arm. It can help evaluate peripheral artery disease. In some circumstances, additional vascular tests are needed because the ABI can be misleading, including in people with certain forms of arterial calcification.

What are pulse points?
Pulse points are locations where an artery is close enough to the skin for its pressure wave to be felt. Common examples include the radial pulse at the wrist, the carotid pulse in the neck, the femoral pulse in the groin, and the popliteal pulse behind the knee. The dorsalis pedis and posterior tibial are the principal pulse sites checked in the foot.
Each location provides information about circulation in a different region of the body. Healthcare professionals select pulse points according to the purpose of the examination, the patient’s condition, and the area of concern. Foot pulses are especially relevant when evaluating lower-extremity circulation and certain vascular conditions.
Why foot pulses matter in people with diabetes
Diabetes can increase the risk of peripheral artery disease and other complications affecting the feet. Assessing pedal pulses is one part of a clinical foot examination, alongside checking skin integrity, sensation, deformities, and wounds. A reduced pulse may prompt additional vascular evaluation.
People with diabetes should not depend on their ability to feel a foot pulse to determine whether their circulation is healthy. Nerve damage can reduce sensation, and vascular problems may not produce obvious symptoms early on. Regular foot examinations and timely assessment of new changes are important.
Foot pulses and peripheral artery disease
Peripheral artery disease (PAD) occurs when narrowed arteries reduce blood flow, most commonly to the legs. It can cause discomfort during walking, pain at rest in more advanced cases, slow-healing wounds, or changes in foot temperature and color. Some people have few obvious symptoms.
Clinicians may check the dorsalis pedis and posterior tibial pulses when PAD is suspected. If the findings or symptoms raise concern, an ABI, Doppler examination, or other vascular investigation may be appropriate. The diagnosis depends on the clinical assessment and relevant test results, not simply on whether a pulse can be felt.
When to seek medical care
Arrange a medical evaluation if you notice a persistent change in foot circulation, a new weak or difficult-to-detect pulse alongside other symptoms, a wound that is not healing, or recurring leg pain when walking. People with diabetes or known vascular disease should take new foot changes seriously.
Seek emergency care immediately if a foot suddenly becomes very painful, cold, pale or blue, numb, or weak. These symptoms may signal acute limb ischemia, a serious reduction in blood supply that needs urgent treatment. Do not delay emergency assessment while trying to find a pulse yourself.
FAQ: Foot Pulses Names
1. What are the two main foot pulse names?
The two main foot pulse names are dorsalis pedis and posterior tibial. The dorsalis pedis pulse is located on the top of the foot, while the posterior tibial pulse is found behind the inner ankle bone.
2. Where is the dorsalis pedis pulse located?
The dorsalis pedis pulse is usually felt on the top of the foot, near the center and just to the outer side of the tendon that extends the big toe. Its precise location can vary naturally.
3. Where is the posterior tibial pulse located?
The posterior tibial pulse is located behind the medial malleolus, the prominent bone on the inner side of the ankle. It is palpated in the soft area between that bone and the Achilles tendon.
4. Is it normal not to feel a pulse on top of the foot?
Sometimes. Anatomical variation or difficulty with manual palpation can make the dorsalis pedis pulse difficult to detect. However, a newly absent pulse or one accompanied by pain, coldness, discoloration, or numbness needs prompt medical assessment.
5. Can a weak foot pulse mean poor circulation?
Yes, a weak pulse can indicate reduced arterial blood flow, including from peripheral artery disease. However, it can also be difficult to detect for other reasons. A healthcare professional can assess the finding and determine whether additional testing is needed.
6. What is a pedal pulse?
A pedal pulse is a pulse detected in the foot. The two principal sites used in routine clinical examinations are the dorsalis pedis artery on the top of the foot and the posterior tibial artery behind the inner ankle.
7. Which test checks blood circulation in the feet?
Healthcare professionals may use Doppler ultrasound to assess arterial blood flow or an ankle-brachial index (ABI) to compare ankle and arm blood pressure. The appropriate test depends on symptoms, examination findings, and medical history.
8. When is an absent foot pulse an emergency?
An absent pulse requires urgent evaluation when it occurs with sudden severe pain, a cold or pale foot, numbness, or new weakness. These symptoms may indicate an acute interruption of blood flow and require emergency medical care.






